


Quick Answer: What Is Subclinical Mastitis?
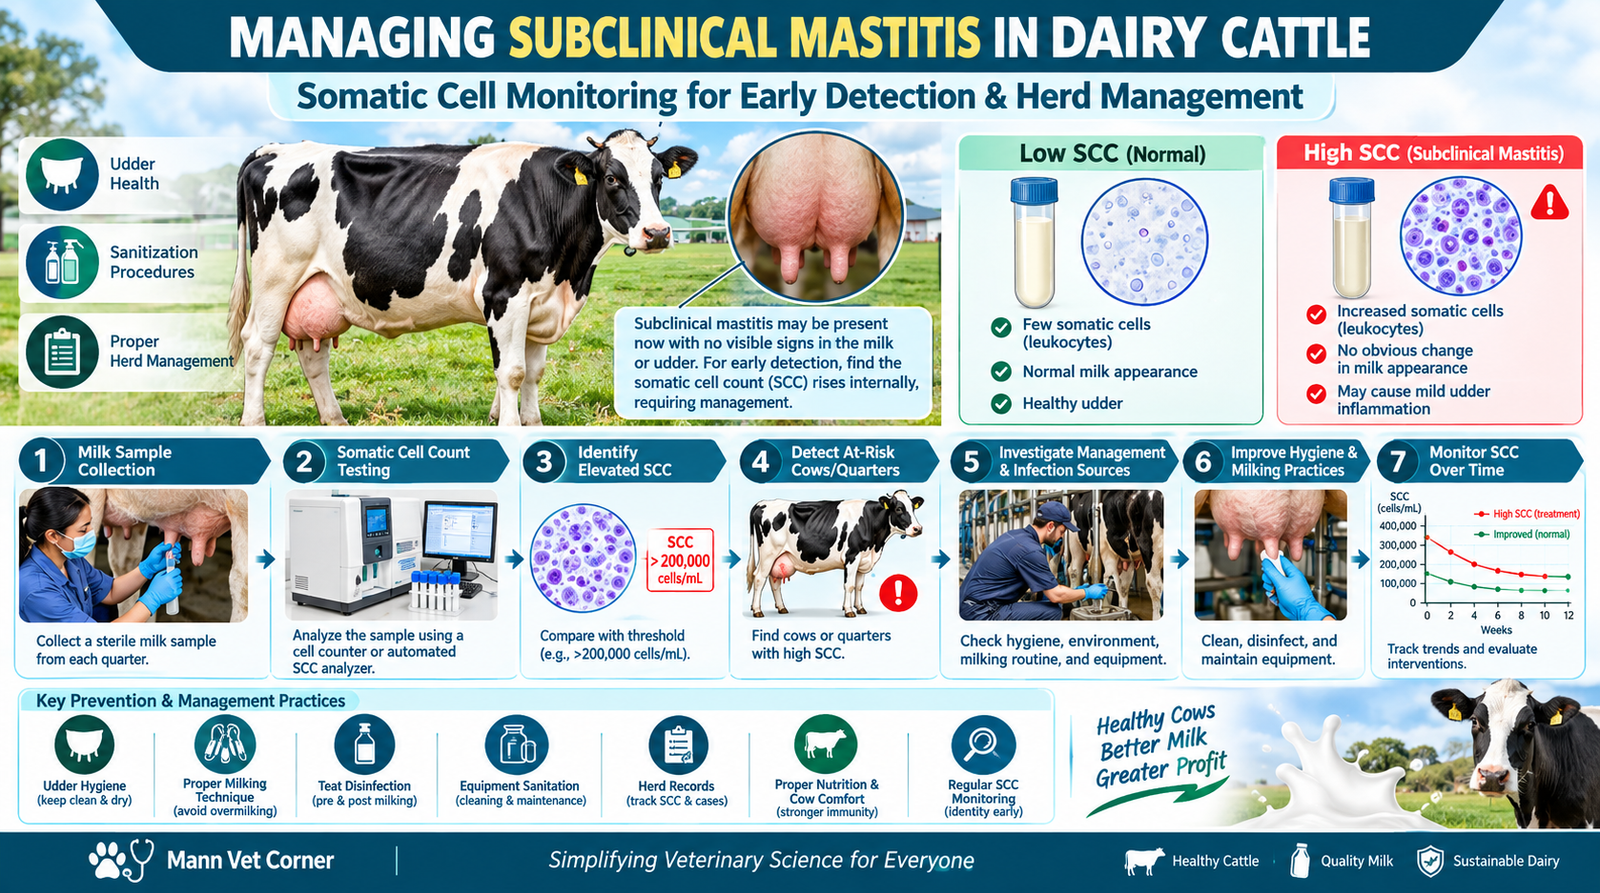
Subclinical mastitis is a bacterial udder infection with no visible signs but elevated somatic cell count (SCC). Somatic cells are white blood cells in milk; healthy quarters produce 50,000-200,000 cells/mL. When infection occurs, SCC rises to 200,000+ cells/mL. Monitoring both bulk milk SCC (BMSCC) and individual cow SCC detects infections early, enabling targeted management decisions, reduced antibiotic use, and improved milk quality. Regular herd testing combined with proper management can reduce subclinical mastitis prevalence by 30-50% within one lactation cycle. Let’s dive into managing subclinical mastitis in dairy cattle through somatic cell monitoring.
Introduction: The Silent Profit Killer in Dairy
Subclinical mastitis is the most costly disease in dairy farming, yet the most invisible. Unlike clinical mastitis with visible clots or discolored milk, subclinical infections occur silently. The cow appears healthy, milk looks normal, but bacteria are multiplying in the udder while somatic cell count climbs.
Economic Impact: A single infected cow costs $300-925 annually in lost production, milk quality penalties, and treatment. On a 200-cow dairy with 40% infection (80 cows), the annual loss exceeds $48,000. Yet this is entirely preventable through proper SCC monitoring and management.
What Is Subclinical Mastitis?
Subclinical mastitis is bacterial infection of the udder without clinical signs. Diagnosis depends entirely on elevated somatic cell count (SCC): individual cow SCC greater than or equal to 200,000 cells/mL, or bulk milk SCC greater than or equal to 200,000 cells/mL, confirmed by milk culture.
How Somatic Cells Indicate Infection
Somatic cells are the cow’s immune system in milk. When bacteria invade the udder, the immune system floods the milk with white blood cells (neutrophils, macrophages, lymphocytes) to fight infection. This cellular response is measurable and predictable, making SCC an excellent infection indicator.
Prevalence: How Common Is It?
Subclinical mastitis is far more common than clinical mastitis. Subclinical prevalence ranges from 30-50% in average herds to 70% in poorly managed facilities. Clinical prevalence is only 3-10%. For every clinical case detected, 10-20 subclinical infections go undetected. Peak periods occur during early lactation (transition stress) and late lactation (chronic infections accumulate).
Understanding Somatic Cell Count: Global Standards
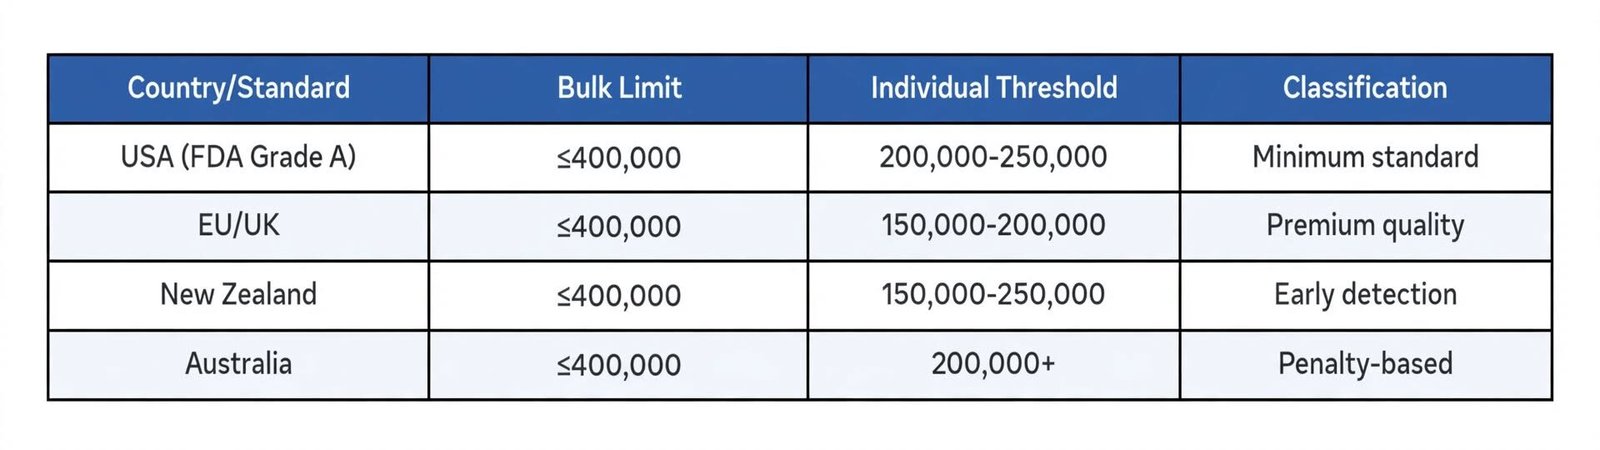
SCC thresholds vary globally. Most developed countries use 200,000 cells/mL as the individual cow threshold and 400,000 cells/mL for bulk milk quality limits:
How to Diagnose Subclinical Mastitis: Testing Methods
Lab SCC Testing: The Gold Standard. Automated flow cytometry or impedance analysis provides the most accurate SCC measurement (±5% accuracy). Results available in 24-48 hours at $0.30-0.75 per sample. Used for official quality assessment and regulatory compliance.
DHI (Dairy Herd Improvement) Testing: Monthly or bi-monthly herd testing provides SCC data by cow, production trends, and genetic information. Cost: $1.50-3.00 per cow per test. Best for long-term herd management and culling decisions.
Rapid Mastitis Test (RMT): On-farm semi-quantitative screening in 60 seconds. Correlates ~75% with lab SCC. Cost: $0.10-0.25 per test. Best for quick screening and colostrum herd assessment.
Milk Culture: Gold standard for bacterial identification. Aerobic culture on blood/MacConkey agar for 48-72 hours identifies specific pathogens and antibiotic sensitivity. Cost: $15-50 per sample. Essential for treatment decision-making.
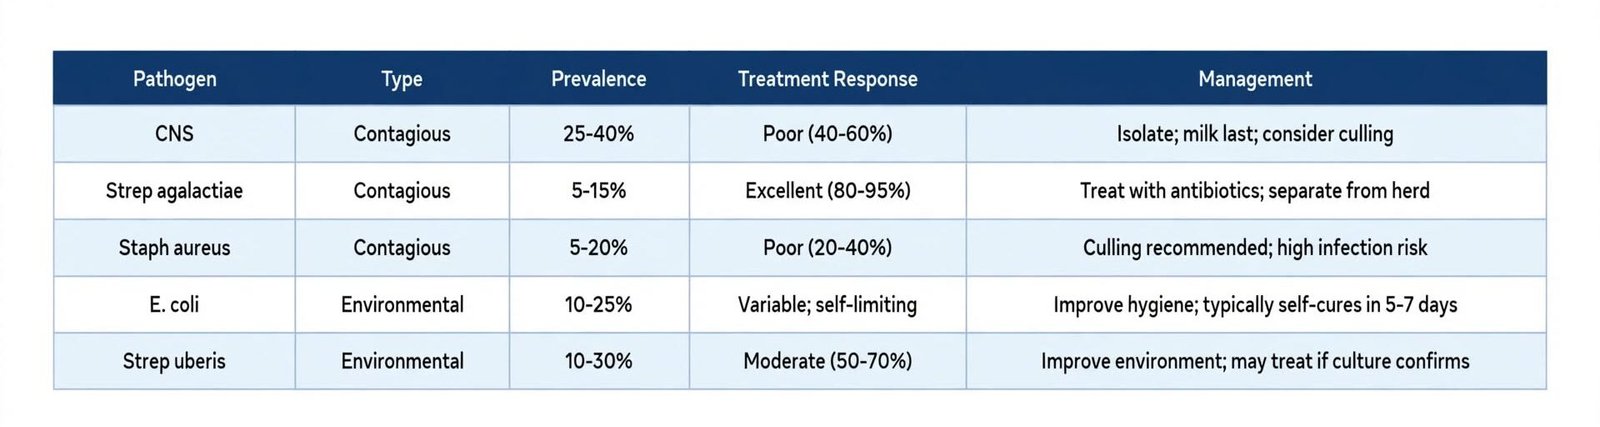
Bacterial Pathogens: Contagious vs. Environmental
Seasonal SCC Patterns: Management Calendar
SCC follows predictable patterns throughout the lactation cycle:
Early Lactation (Months 1-2): SCC is HIGHEST (400-800K). Transition stress, colostrum management issues, and peripartum infections dominate. Action: Strict colostrum protocols, RMT screen fresh cows before main herd entry, investigate high-SCC cases.
Peak Lactation (Months 3-4): SCC is LOWEST (150-250K). High milk volume dilutes cell counts and most infections have resolved. Action: Establish baseline SCC data, maintain excellent hygiene, identify baseline problem cows.
Mid Lactation (Months 5-7): SCC RISING (250-350K). Infections accumulate over time. Action: Increase testing to monthly frequency, identify rising-SCC cows, culture suspicious cases.
Late Lactation (Months 8-10): SCC is HIGH (350-500K+). Chronic infected cows dominate, milk volume is low (cells concentrate), environmental stress is high. Action: Plan drying-off decisions, culture all high-SCC cows, evaluate selective culling.
Economic Impact: Cost Per Infected Cow
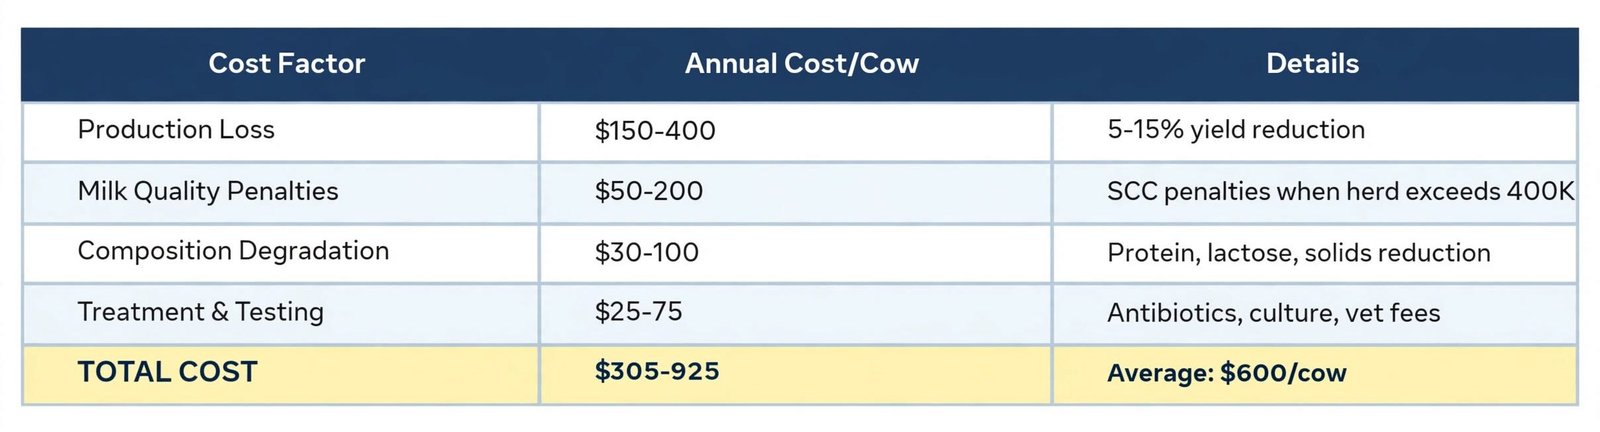 Herd-Level Example: 200-cow dairy with 40% infection (80 cows) at $600/cow = $48,000 annual loss.
Prevention Strategies: Reducing Subclinical Mastitis
Milking Hygiene (Non-Negotiable): Wash and dry udders, strip foremilk, wear gloves, practice post-dip teat dipping with iodine or chlorhexidine (30-second contact), milk healthy cows first and high-SCC cows last, maintain equipment with quarterly audits.
Environmental Control: Keep calving areas clean and dry, manage bedding (deep straw or sand, change frequently), maintain clean parlors, segregate infected cows into separate milking groups.
Colostrum Management (Critical): Separate colostrum herd housing, screen all fresh cows with RMT before main herd entry, milk culture suspicious quarters, withhold colostrum milk from vat for minimum 8 milkings.
Nutrition: Support immune function during transition with adequate energy and balanced amino acids; supplement vitamin E (1,000-2,000 IU/day) and selenium (0.3 mg/day) to reduce SCC by 20-30%.
Genetic Selection: Select sires with low SCS (Somatic Cell Score) proofs; choose cows with good udder conformation and appropriate teat length (40-50 mm) to reduce infection susceptibility.
Frequently Asked Questions
Q1: What is the difference between clinical and subclinical mastitis?
Clinical mastitis shows visible signs: clots, flakes, discolored milk, udder swelling, or heat. Subclinical mastitis is asymptomatic with normal-appearing milk but elevated SCC (>200K cells/mL). Subclinical cases are 5-20 times more common and cause 80% of production losses.
Q2: How often should I test SCC?
Minimum: Bi-monthly herd testing (DHI recording ~4 tests per lactation). Daily bulk tank monitoring via tanker data alerts to sudden spikes. Farms with >400K BMSCC should test monthly until trending down.
Q3: Should I treat all high-SCC cows with antibiotics?
No. Blanket treatment is ineffective and drives antibiotic resistance. Obtain milk culture first. Only Streptococcus agalactiae (80-95% cure) justifies lactation therapy. CNS, Staph aureus, and E. coli respond poorly (20-60% cure) and are better managed through isolation or culling.
Q4: What SCC level warrants culling?
Chronic infections (>400K for 3+ consecutive tests), Staph aureus infections (poor prognosis, high transmission risk), or repeat offenders with low genetic merit should be culled. Valuable genetics might be retained longer, but chronically infected low-producers should be culled immediately.
Q5: Is high SCC normal in late lactation?
Yes. SCC naturally peaks in late lactation (months 8-10) due to infection accumulation, lower milk volume, and fewer young cows. Plan accordingly: dry off high-SCC cows early, focus dry-cow therapy on high-risk animals, prepare replacement heifers.
Q6: Can I eliminate CNS from my herd?
CNS eradication is extremely difficult because it colonizes cow skin and persists environmentally. Realistic goal: Reduce prevalence through aggressive hygiene, milking isolation, and genetic selection. Most well-managed herds still have 20-30% CNS prevalence.
Q7: What is a realistic SCC reduction target?
Starting >500K BMSCC: Aim to reduce 50-80K/month over 6-12 months through systematic hygiene and treatment. Starting 300-400K: Target <250K within 4-6 months. Most well-managed herds stabilize at 150-250K BMSCC long-term.
Q8: How do I detect missed clinical cases?
Watch for sudden bulk tank SCC spikes (>50K jump in 24 hours, especially in small herds). Implement routine pre-milking stripping into a strip cup (detects 70-80% of clinical cases), post-milking teat inspection, daily pen walks, and rapid response to BMSCC spikes.
Q9: What is the best on-farm rapid test?
RMT (Rapid Mastitis Test) is most practical: 60-second screening with ~75% correlation to lab SCC, costs $0.10-0.25 per test. CMT (California Mastitis Test) is cheaper ($0.15-0.20) but observer-dependent (~60% accuracy). Use RMT for screening; confirm with lab testing for management decisions.
Q10: What is the ROI of SCC management programs?
Investment: $2,000-5,000 annually (testing, nutrition, equipment). Returns: $25,000-45,000 in saved losses and improved premiums. ROI ratio: 4:1 to 7:1. Excellent investment in herd health and profitability.
Conclusion: Building a Low-SCC Herd
Subclinical mastitis is preventable. Somatic cell count monitoring combined with excellent milking hygiene, environmental management, proper nutrition, and strategic culling reduces bulk tank SCC to <250K within 12-18 months and maintains that level long-term.
Next Steps for Your Farm:
- Schedule a veterinary herd health visit for SCC assessment and reduction plan
- Enroll in DHI testing for monthly SCC tracking and genetic data
- Audit milking protocols: udder prep, post-dip compliance, equipment performance
- Review transition cow nutrition and immune-support strategies
- Establish data-driven culling policy based on SCC, production, and genetics





Leave a Reply